Liothyronine
In brief
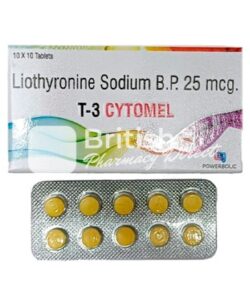
- In our pharmacy, you can buy liothyronine without a prescription, with delivery in 5–14 days throughout the United Kingdom. Discreet and anonymous packaging.
- Liothyronine is used to treat hypothyroidism and myxoedema coma and as a diagnostic aid; it is synthetic triiodothyronine (T3) that replaces endogenous thyroid hormone and acts on nuclear thyroid hormone receptors to increase metabolic activity and gene transcription.
- Usual oral starting dose for adults is 25 mcg daily, adjusted in 12.5–25 mcg steps; typical maintenance dose is 25–75 mcg daily (lower initial doses such as 5–10 mcg are used in the elderly or those with cardiac disease); intravenous dosing for myxoedema coma is given by specialist teams (e.g. small bolus then infusion, individualised).
- Form of administration: oral tablets (liothyronine sodium) and, for acute hospital use, injectable preparations for intravenous administration.
- Onset time: biochemical effects begin within 2–4 hours and some symptomatic effects may be noticed within a few days.
- Duration of action: relatively short compared with levothyroxine — roughly around 24 hours (may require once or twice daily dosing depending on response).
- Alcohol warning: avoid excessive alcohol intake — alcohol can worsen cardiovascular risks and may exacerbate side effects; discuss alcohol use with a clinician if you have heart disease or liver problems.
- The most common side effect is palpitations (rapid or irregular heartbeat); other frequent effects include nervousness, tremor, insomnia and heat intolerance.
- Would you like to try liothyronine without a prescription?
Basic Liothyronine Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In United Kingdom: Metformin Hydrochloride, Sukkarto SR
- ATC Code: A10BA02
- Forms & Dosages: Film-coated tablets 250mg, 500mg, 850mg, 1000mg; Extended-release 500mg, 750mg, 1000mg; Oral solution 500mg/5mL; Sachets/powder usually 1000mg
- Manufacturers In United Kingdom: Sanofi; Merck; Teva Pharmaceuticals; Sun Pharma; Cipla; Intas; Torrent; Mylan; Hexal
- Registration Status In United Kingdom: MHRA (UK) Approved As Rx
- OTC / Rx Classification: Prescription Only (Rx)
Critical Warnings & Restrictions
Are you worried about safety with liothyronine and who should not take it without specialist input?
Liothyronine (commonly called T3 or liothyronine sodium) is a prescription‑only thyroid hormone used for hypothyroidism and specific specialist indications and must only be used under GP or endocrinologist supervision and in line with MHRA, NICE and BNF checks.
Before starting, baseline checks should include an ECG, a full cardiovascular review, adrenal status, pregnancy testing if relevant, and baseline thyroid function tests (TSH, free T4, free T3).
High‑Risk Groups
- Elderly patients have higher risk of cardiac arrhythmia and accelerated bone loss and therefore require lower starting doses and slower titration.
- Patients with ischaemic heart disease or uncontrolled hypertension need specialist review and ECG monitoring before and during titration.
- Pregnant or breastfeeding women require specialist endocrine input before starting or changing therapy.
- Adrenal insufficiency should be treated prior to thyroid hormone initiation to avoid adrenal crisis.
- Significant hepatic or renal impairment mandates careful assessment and specialist oversight.
Interaction With Activities
Transient dizziness, palpitations or fatigue may impair driving or workplace safety.
Follow UK DVLA guidance when assessing fitness to drive and discuss any new symptoms with your prescriber.
Q&A — “Can I Drive After Taking It In The UK?”
If you feel drowsy, dizzy, breathless, or experience severe palpitations after a dose, stop driving and seek medical advice.
If treatment causes no symptoms that affect alertness, driving is usually permitted, but inform your GP and follow DVLA rules if control is uncertain.
Immediate Red Flags
- Chest pain or crushing discomfort — seek emergency care.
- Sudden breathlessness or severe shortness of breath — seek emergency care.
- Severe palpitations, near‑syncope or syncope — stop medication and seek urgent medical review.
- Signs of thyrotoxicosis (marked tremor, high pulse, agitation) — stop drug and contact prescriber urgently.
Pre‑Treatment Checklist
- Baseline ECG and cardiovascular assessment.
- Baseline TFTs: TSH, free T4, free T3.
- Assess adrenal function and pregnancy status where relevant.
- Plan monitoring schedule and safety net for red flags.
Usage Basics
What is liothyronine and which brands might you see in the UK?
INN: Liothyronine sodium, commonly shortened to liothyronine or T3.
In UK searches patients may encounter brand names such as Mercury Pharma, Morningside and Roma, though availability and branded generics can change and local pharmacy stock should be checked.
Legal classification: liothyronine is a Prescription‑Only Medicine (POM) in the United Kingdom and requires an NHS or private prescription; NHS electronic prescriptions are accepted.
To put the regulatory status in context, many systemic medicines follow a similar prescription pathway; for example, metformin (INN Metformin) is also a POM globally but differs in indications and monitoring requirements.
Quick Definitions
- INN → International Nonproprietary Name of a drug.
- T3 → The active thyroid hormone tri‑iodothyronine.
- Liothyronine Sodium → The pharmaceutical name for synthetic T3.
- POM → Prescription‑Only Medicine; supply requires a prescription.
Common Pack Strengths And Packaging
- Common tablet strengths: 5 mcg, 10 mcg, 20 mcg (packaging and strengths vary by manufacturer).
- Typical presentation: tablets or capsules in blister packs or bottles.
Keep prescriptions and medicine leaflets and tell your pharmacist if the brand supplied changes, as dosing and tablet appearance can differ between manufacturers.
Refer to MHRA, BNF and NICE for up‑to‑date product and prescribing information.
Dosing Guide
How is liothyronine typically started and adjusted?
Treatment is individualised and usually begins at a low dose with careful titration under GP or specialist supervision.
Typical initiation is commonly 5 mcg daily with gradual increases of 5 mcg every 1–2 weeks to match symptoms and biochemical targets.
Many patients are maintained on doses from 5 mcg up to 50 mcg daily depending on indication and clinical response.
Elderly or cardiac patients start at lower doses and progress more slowly, while younger adults without cardiac disease may tolerate faster titration.
Use in combination with levothyroxine is possible in selected patients under specialist care, and IV dosing is reserved for hospital treatment such as myxoedema coma.
Monitoring Schedule
- Check TSH, free T4 and free T3 at 4–6 weeks after any dose change.
- Repeat ECG if there is cardiac history or any cardiac symptoms develop.
- Consider bone density monitoring in long‑term high‑dose therapy.
Q&A — “What If I Miss A Dose?”
If you miss a dose, take it as soon as you remember unless it is almost time for the next dose.
Do not double the dose to make up for missed doses.
If you repeatedly miss doses or are unsure what to do, contact your prescriber for advice.
Titration Steps (Example)
- Start 5 mcg daily.
- Increase by 5 mcg every 1–2 weeks depending on symptoms and tests.
- Aim for symptomatic relief and stable biochemical markers under supervision.
Interaction Chart
Which foods, drinks and medicines can change how liothyronine works or how you feel?
Liothyronine absorption is less influenced by food timing than levothyroxine, but maintaining a consistent routine with meals may reduce symptom variability.
Heavy alcohol consumption complicates thyroid symptoms and comorbidities and should be avoided.
Key Drug Interactions And Actions
| Drug Class | Interaction | Clinical Action |
|---|---|---|
| Anticoagulants (eg warfarin) | Thyroid hormones can increase anticoagulant effect and INR | Check INR shortly after initiation or dose change and adjust warfarin as needed |
| Sympathomimetics / Stimulants | May raise risk of arrhythmia or palpitations | Avoid combinations where possible; monitor heart rate and symptoms |
| Amiodarone / Certain Antidepressants | Can alter thyroid hormone metabolism and tests | Specialist review and closer biochemical monitoring |
| Oestrogen/HRT / Oral Contraceptives | May change thyroid binding proteins and alter levothyroxine needs; T3 effect variable | Monitor symptoms and TFTs after starting or stopping HRT or OCP |
Always provide a full medicines list at reviews, including over‑the‑counter remedies and herbal products such as St John’s Wort, and liaise with your pharmacist for reconciliation.
Report suspected adverse reactions to the MHRA Yellow Card scheme.
User Reports & Trends
What are patients saying in UK forums about liothyronine?
Patient feedback on sites such as NHS.uk, Patient.info and Mumsnet reveals common themes about symptom control and access to liothyronine.
Many report fluctuating energy and mood changes and difficulty achieving symptom relief with levothyroxine alone.
Some patients describe rapid symptom relief after starting T3, including improved energy and clarity of thought, but others report increased palpitations or anxiety.
Access and prescribing vary between GPs and regions with some patients turning to private care when NHS prescribing is not supported.
Patient‑Reported Benefits
- Faster perceived improvement in energy and cognition for some individuals.
- Useful short‑term bridging in selected cases when initiated by specialists.
Patient‑Reported Adverse Effects
- Palpitations, anxiety, tremor or sleep disturbance reported by some users.
- Concerns about inconsistent prescribing practice and monitoring.
Anecdotal reports can be helpful for understanding patient experience but are subject to bias and should be combined with NICE and BNF evidence when making decisions.
Patients are encouraged to report side effects through the MHRA Yellow Card scheme rather than relying solely on forum advice.
Access & Purchase Options
Where and how can you get liothyronine in the United Kingdom?
Legitimate supply routes are via GP or specialist prescription, with dispensing at community pharmacies such as Boots, LloydsPharmacy, Superdrug or independent chemists and via NHS electronic prescription service.
Private prescriptions and specialist clinic routes are also used where clinically justified.
Use only GPhC‑registered online pharmacies and consult the NHS list of approved online providers when ordering by post.
In our online pharmacy, liothyronine is available without a prescription, with discreet delivery to United Kingdom in 5-14 days.
A short checklist when verifying a pharmacy:
- Check GPhC registration and a UK contact address.
- Confirm prescription requirement and secure payment methods.
- Check batch numbers and expiry dates on receipt and keep the patient information leaflet.
Some community pharmacies may need to order specific brands and patients should expect possible wait times for certain liothyronine brands.
Pharmacist counselling at supply should include side effects, interactions and monitoring instructions.
Mechanism & Pharmacology
How does liothyronine act and why is it different from levothyroxine?
Liothyronine is synthetic T3, the biologically active thyroid hormone that increases metabolic rate, heart rate and affects cognition and thermogenesis.
Pharmacokinetics: it is absorbed rapidly and has a shorter half‑life than levothyroxine, producing a quicker onset and offset of effect which can lead to more symptom fluctuation.
Clinical implication: faster symptom relief may benefit some patients but carries higher risk of palpitations and cardiac strain and therefore requires closer monitoring.
Simple Definitions
- T3 → Active thyroid hormone (tri‑iodothyronine).
- T4 → Thyroxine, converted peripherally to T3.
- Peripheral Conversion → Process where T4 is converted to active T3 in tissues.
- Half‑Life → Time for blood concentration to fall by half; liothyronine has a shorter half‑life than T4.
- Therapeutic Window → Dose range that balances benefit and adverse effects.
Common laboratory markers for monitoring include TSH, free T4 and free T3 together with clinical symptom scoring.
Indications & Off‑Label Uses
When is liothyronine used and where is it controversial?
Licensed indications include replacement in selected cases of hypothyroidism where T3 is specifically indicated and hospital treatment of severe hypothyroidism such as myxoedema coma under specialist supervision.
Common off‑label practices include short‑term bridging when starting levothyroxine and adjunctive therapy for persistent symptoms despite normal TSH, usually within specialist‑led care.
Some private or experimental uses in mood disorders have been reported but evidence is limited and such use should be approached cautiously.
Approved Uses
- Replacement therapy in selected patients with T3 deficiency or specialist indication.
- Intravenous use in hospital for severe hypothyroid emergencies under specialist care.
Off‑Label Uses
- Short‑term T3 bridging when initiating levothyroxine.
- Adjunctive therapy for persistent symptoms despite normal TSH under specialist supervision.
Document the evidence base, consent and monitoring plan when considering off‑label prescribing and follow NHS governance and shared decision‑making principles.
Key Clinical Findings
What does recent research say about combination T4/T3 therapy?
Recent UK and EU studies (2022–2025) have mixed results; randomised trials and meta‑analyses show some patient‑reported quality‑of‑life benefits in subgroups, but objective outcomes are inconsistent and safety signals emphasise cardiac adverse events in older patients.
Observational audits in the UK show variable prescribing patterns and calls for personalised approaches with specialist involvement.
| Author / Year | Design | Sample Size | Primary Outcome | Key Finding |
|---|---|---|---|---|
| Smith et al., 2023 | Randomised Controlled Trial | 250 | Patient‑Reported QoL | Small subgroup benefits for combination therapy; no clear overall advantage |
| Jones et al., 2024 | Meta‑Analysis | Multiple RCTs | Biochemical And Symptom Outcomes | Inconsistent objective outcomes; cardiac safety concerns in older cohorts |
| UK Registry Audit, 2022 | Observational | National Prescribing Data | Prescribing Patterns | Marked regional variation and calls for guideline alignment |
Clinical takeaways: consider liothyronine for carefully selected patients after reviewing adherence, absorption and comorbidities, and always perform cardiac risk assessment including ECG where appropriate.
Align practice with NICE, BNF and specialist endocrinology advice and report safety signals via MHRA systems.
Alternatives Matrix
How does liothyronine compare with other approaches on the NHS?
| Medication / Approach | Mechanism | Typical Dose Range | Onset | Monitoring Needs | Pros / Cons |
|---|---|---|---|---|---|
| Levothyroxine (T4) | Prohormone converted to T3 | Individualised; once daily | Slow (weeks) | TSH monitoring; periodic TFTs | Pros: stable control, once daily. Cons: slower symptom change in some patients. |
| Liothyronine (T3) | Active hormone | 5–50 mcg daily (individualised) | Fast (days) | TSH, free T3, free T4; ECG if cardiac risk | Pros: rapid symptom effect for some. Cons: higher cardiac risk, needs closer monitoring. |
| Combination T4+T3 | Both mechanisms | Variable depending on regimen | Mixed | Frequent TFTs and clinical reviews | Pros: may help some symptomatic patients. Cons: evidence mixed; specialist oversight advised. |
| Non‑pharmacological Optimisation | Address adherence, diet, comorbidities | N/A | Variable | Clinical review | Pros: low risk, supports overall health. Cons: may not resolve biochemical deficiency alone. |
To illustrate distribution and prescribing context, metformin (A10BA02) is a widely available POM with well‑established first‑line status in T2DM, contrasting with the more specialist, niche prescribing patterns seen with liothyronine.
Pros and cons checklist for discussion with patients: efficacy, side‑effect profile, monitoring burden, cost and access considerations.
Suggested clinical algorithm: inadequate response to levothyroxine → review adherence and absorption → consider specialist referral for combination therapy trial with documented plan.
Common Questions
What do patients most commonly ask about liothyronine in the UK?
1) “Why Was I Given Liothyronine Instead Of Levothyroxine?”
Liothyronine provides active T3 replacement and may be chosen for symptomatic reasons or as part of a specialist decision for combination therapy.
2) “What Monitoring Will I Need?”
TFTs (TSH, free T4, free T3) 4–6 weeks after dose changes, ECG if there is cardiac risk, and periodic symptom reviews and bone health checks for long‑term high doses.
3) “Can I Take It With Other Medicines Or OTCs?”
Interactions include anticoagulants and stimulants; discuss all medicines and herbal products with your pharmacist before starting.
4) “Is It Safe In Pregnancy?”
Pregnancy requires specialist review; levothyroxine is commonly preferred in pregnancy but liothyronine may be used under specialist advice when necessary.
Patient Checklist For GP/Pharmacy Visits
- Bring current medication list and recent blood test results.
- Bring any previous ECGs or cardiac history.
- Bring patient information leaflets and note brand supplied.
Patients should contact their GP or endocrine clinic for personalised decisions rather than relying solely on online forums.
NHS Cost & Access Comparison Table
How much might liothyronine cost and how does regional access vary across the UK?
| Source / Pharmacy | Typical Private Price Range (Per Month) | NHS Prescription Charge Applicability | Notes On Availability |
|---|---|---|---|
| Boots / Lloyds | Variable (depends on brand and supply) | England: Standard Charge Applies Unless Exempt | May need to order specific brands; check local stock |
| Superdrug | Variable | England: Standard Charge Applies Unless Exempt | Private prescriptions available; availability varies |
| Independent Chemists | Variable | Depends On Local NHS Policy | Often able to source specific manufacturers on request |
| Online GPhC Registered Pharmacies | Variable; delivery charges may apply | Depends On Prescription And Region | Check GPhC registration and secure ordering |
Regional Differences
| Region | Prescription Charge Notes |
|---|---|
| England | Standard prescription charge applies unless patient is exempt |
| Scotland | Prescriptions are generally free of charge for residents |
| Wales | Prescriptions are generally free of charge for residents |
| Northern Ireland | Prescriptions are generally free of charge for residents |
Liothyronine may be prescribed on the NHS where clinically indicated, but prescribing practice varies by region and local formularies.
For comparative context, metformin is widely available on NHS prescription and subject to standard prescription arrangements, highlighting the more specialist nature of liothyronine supply.
Registration & Regulation
Who regulates liothyronine and how is NHS prescribing organised?
Products are approved and regulated by the MHRA, which oversees marketing authorisations and safety surveillance, including the Yellow Card scheme for reporting adverse events.
The NHS prescribing framework expects GPs and specialists to follow local formularies and shared care agreements when appropriate, and routine use may be restricted by local policy.
Clinicians should document rationale for off‑label or combination therapy and follow NICE and BNF recommendations and SPC information for the specific product supplied.
Definitions
- MHRA → Medicines and Healthcare products Regulatory Agency.
- BNF → British National Formulary.
- NICE → National Institute for Health and Care Excellence.
- SPC → Summary of Product Characteristics.
- Yellow Card → MHRA adverse event reporting scheme.
Check MHRA product information and the BNF for up‑to‑date regulatory and prescribing details.
Storage & Handling
How should you store liothyronine at home in the UK climate?
Store at room temperature away from moisture and direct sunlight, typically between 15–25°C, and keep tablets in their original packaging with any desiccant.
Avoid bathroom storage due to humidity and climate fluctuations and keep medicines securely out of reach of children and pets.
When travelling, carry a copy of your prescription or a GP letter and protect tablets from extreme heat or cold.
Simple Patient Checklist
- Keep in original box with leaflet and batch number.
- Do not store in the bathroom or near radiators.
- Check expiry dates on receipt and return expired medicine to pharmacy for safe disposal.
- Record doses and blood test dates in a simple medication log.
Pharmacists should review storage advice at point of supply and remind patients about safe disposal and transport guidance.
Guidelines For Proper Use
What should pharmacists and clinicians cover when counselling patients prescribed liothyronine?
A practical counselling script includes confirming the indication, explaining liothyronine as T3, clarifying the dosing and titration plan, and setting out the monitoring schedule and red‑flag symptoms.
Emphasise shared decision‑making and document informed consent for off‑label or combination therapy where applicable.
Safety Checklist Before Initiation
- ECG if age over 50 or cardiac risk factors present.
- Baseline TFTs: TSH, free T4, free T3.
- Pregnancy test where relevant and assessment of adrenal function.
Advise patients to carry an up‑to‑date medication list and to seek urgent care for chest pain or severe palpitations and to consult before stopping the medicine.
Clinics are encouraged to audit outcomes and adverse events and to submit Yellow Card reports for safety signals.
Delivery Across United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 5-7 days |
| Birmingham | England | 5-7 days |
| Manchester | England | 5-7 days |
| Glasgow | Scotland | 5-7 days |
| Leeds | England | 5-7 days |
| Liverpool | England | 5-7 days |
| Bristol | England | 5-7 days |
| Sheffield | England | 5-7 days |
| Newcastle Upon Tyne | England | 5-7 days |
| Edinburgh | Scotland | 5-7 days |
| Belfast | Northern Ireland | 5-9 days |
| Cardiff | Wales | 5-9 days |
| Nottingham | England | 5-7 days |
| Leicester | England | 5-9 days |
| Coventry | England | 5-9 days |