Tobradex
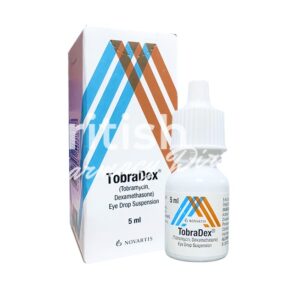
In brief
- Tobradex is a prescription-only medicine (POM) in the UK.
- Tobradex is used to treat and prevent steroid‑responsive eye inflammation when a bacterial infection is suspected or confirmed and for post‑surgical prophylaxis; it combines tobramycin (an aminoglycoside antibiotic that inhibits bacterial protein synthesis) with dexamethasone (a corticosteroid that reduces inflammation via glucocorticoid receptor‑mediated suppression of inflammatory mediators).
- The usual dosage is 1–2 drops in the affected eye(s) every 4–6 hours, which may be increased to every 2 hours initially in severe cases; typical treatment courses last 5–14 days (up to about 24 days with review by a clinician).
- Administered topically as ophthalmic drops (suspension).
- Symptomatic relief may begin within hours, with clinical improvement commonly seen within 24–48 hours after starting treatment, depending on the condition treated.
- The effect of a single dose typically lasts about 4–6 hours (hence regular dosing at that interval); the overall treatment course is usually 5–14 days for acute infections or as advised for post‑operative prophylaxis.
- There is no specific alcohol restriction with topical Tobradex; systemic absorption is minimal, so moderate alcohol intake is not known to interact, though avoid excessive alcohol if generally unwell and always follow your clinician’s advice.
- The most common side effect is local eye irritation or burning; other possible effects include redness, eyelid itching or swelling, and with prolonged steroid use a rise in intraocular pressure or cataract formation.
- Would you like to try Tobradex without a prescription?
Basic Tobradex information
- INN (international nonproprietary name): Tobramycin/dexamethasone.
- Brand names available in the United Kingdom: Tobradex (supplied as a 5 mL dropper bottle by Novartis/Alcon in the UK market).
- ATC code: S01CA01 (Corticosteroids and antiinfectives in combination for ophthalmological use).
- Forms and dosages: Ophthalmic suspension — tobramycin 3 mg/mL + dexamethasone 1 mg/mL in 5 mL.
- Manufacturers in the United Kingdom: Novartis Pharmaceuticals UK Ltd.
- Registration status in the United Kingdom: Approved by the MHRA.
- OTC / Rx classification: Prescription-only medicine (POM) in the UK.
Critical warnings, restrictions and patient protection (UK first)
Key safety points:
- Tobradex is a fixed‑dose ophthalmic combination of tobramycin (an aminoglycoside antibiotic) and dexamethasone (a corticosteroid).
- Tobradex is a prescription‑only medicine and is MHRA‑approved for use in the United Kingdom.
- Do not use Tobradex if a viral eye infection (for example herpetic keratitis), fungal eye infection, or tuberculous eye disease is suspected or possible.
- Stop treatment and seek urgent care for severe eye pain, marked loss of vision, new floaters, purulent discharge, or worsening redness.
- Report any suspected adverse reactions via the MHRA Yellow Card scheme.
High‑risk groups
- Elderly — monitor intraocular pressure and be alert to steroid‑related cataract risk with prolonged therapy.
- Children under 2 years — safety data are limited and use should be a specialist decision under ophthalmology guidance.
- Pregnant or breastfeeding women — topical ocular use leads to minimal systemic absorption, but consult the obstetrician or ophthalmologist before use.
- Patients with glaucoma or known steroid response — measure intraocular pressure if therapy is prolonged and monitor for pressure rises.
Interaction with activities
- Transient blurring or minor irritation may occur after instillation; do not drive or operate machinery until vision is clear.
- Employers and occupational health should consider risk assessments where precision vision is required following eye‑drop use.
Can I drive after taking it in the UK?
Short answer: Only if vision is normal and not impaired by blurring after instillation.
If drops cause blurred vision, wait until vision clears before driving, to meet DVLA and licensing safety obligations.
If visual disturbance is persistent, inform the clinician or pharmacist promptly.
Usage basics: names, classification and UK availability
INN and UK brands
- INN: tobramycin/dexamethasone.
- Brand in the UK: Tobradex, typically supplied as a 5 mL dropper bottle by Novartis/Alcon.
Legal classification and supply
- Tobradex is prescription‑only (POM) and is MHRA‑approved for use in the United Kingdom.
- Patients normally receive Tobradex following a GP, hospital ophthalmology clinic, or private prescription from an optometrist, GP or ophthalmologist.
- Community pharmacists provide counselling on correct use, storage and side‑effect monitoring; some secondary‑care trusts supply under local arrangements.
Practical note
- Check the manufacturer leaflet for excipient allergies such as preservatives if the patient has sensitivities.
- Confirm the MHRA product information or SPC for local details and up‑to‑date guidance.
Dosing guide and adjustment (NHS‑centred)
Standard regimens
- Adults and elderly: 1–2 drops in the affected eye(s) every 4–6 hours as standard.
- In more severe cases, the frequency may be increased to every 2 hours initially under prescriber instruction.
- Typical course duration is 5–14 days, with review; complex or post‑operative cases may be continued with specialist review up to about 24 days.
Adjustments for comorbidities
- No routine renal or hepatic dose adjustments are required for topical ocular use because systemic absorption is minimal.
- Exercise caution in patients with severe systemic disease and where systemic exposure is a concern.
- Monitor intraocular pressure in patients with glaucoma or known steroid responders when therapy is prolonged.
- Use in children under 2 years is generally not recommended without specialist oversight due to limited safety data.
What if I miss a dose?
Apply the missed drop as soon as you remember unless it is almost time for the next scheduled dose.
Do not double up to make up a missed dose.
If unsure, contact your pharmacist or prescriber for advice.
For accidental multiple instillations, rinse the eye with water and seek advice if there are concerns.
Interaction chart and reporting (how to present to patients)
Food, drink and lifestyle
- Topical ocular absorption is minimal, so routine food or alcohol interactions are unlikely with Tobradex.
- Counsel that systemic aminoglycoside interactions are not expected at standard topical dosing.
Common drug conflicts and safety signals
| Drug | Interaction | Severity |
|---|---|---|
| Other ocular corticosteroids | Increases overall steroid burden and IOP risk if used concurrently | Moderate to high |
| Other topical aminoglycosides | Potential increased local toxicity and irritation with combined topical aminoglycoside use | Moderate |
| Systemic ototoxic/nephrotoxic aminoglycosides | Check if systemic exposure is possible; theoretical additive aminoglycoside toxicity | Low (rare with topical use) |
- Advise prescribers to check systemic aminoglycoside use only if systemic exposure is plausible.
- Pharmacies and clinics should document and report ocular pressure rises or suspected secondary infections.
- Encourage reporting of suspected adverse reactions to the MHRA Yellow Card scheme.
Legal status and availability in the UK
Tobradex is a prescription-only medicine (POM) in the UK.
Our online pharmacy can provide discreet delivery across the United Kingdom, with typical delivery windows noted below.
Mechanism of action and pharmacology (clear lay + clinical)
Simplified explanation
- Tobramycin: bactericidal aminoglycoside that inhibits bacterial protein synthesis by binding to the 30S ribosomal subunit.
- Dexamethasone: potent corticosteroid that reduces inflammation by modulating gene expression and decreasing inflammatory mediators.
Clinical terms
- The combined formulation is used where steroid‑responsive inflammation and suspected or confirmed bacterial infection coexist, and frequently for post‑operative prophylaxis.
- ATC classification: S01CA01 — corticosteroids and antiinfectives in combination for ophthalmological use.
Definitions
- Aminoglycoside → An antibiotic class that kills bacteria by stopping protein production in susceptible organisms.
- Glucocorticoid → A steroid hormone class that reduces inflammation by altering cellular signalling and gene transcription.
- Steroid‑responsive inflammation → Inflammation that improves when corticosteroids reduce swelling and immune activity in eye tissues.
Indications and off‑label practice in UK care
MHRA‑approved indications
- Treatment of steroid‑responsive ocular inflammation where bacterial infection is suspected or confirmed.
- Prevention and treatment in post‑surgical ocular inflammation with risk or presence of bacterial contaminants.
- Use is particularly common in acute bacterial conjunctivitis with marked inflammatory response and in post‑operative care following cataract or other anterior segment surgery.
Off‑label practices
- Specialist paediatric use (under 2 years) may occur under ophthalmology guidance when benefits outweigh risks.
- Clinicians sometimes opt for a combined product short‑term when both anti‑infective and anti‑inflammatory control are needed simultaneously, with close monitoring for steroid complications.
- Always document the rationale for any off‑label use, inform the patient or guardian and schedule appropriate follow‑up such as intraocular pressure checks for prolonged therapy.
Alternatives matrix (NHS prescribing choices)
NHS alternatives
| Product | Active ingredients | Steroid potency / class | Antibiotic class | Typical NHS use case |
|---|---|---|---|---|
| Maxitrol | Neomycin + polymyxin B + dexamethasone | Dexamethasone (potent) | Aminoglycoside + polymyxin (broad topical) | Post‑op inflammation where neomycin is tolerated |
| Tobrex | Tobramycin alone | No steroid | Aminoglycoside | Confirmed bacterial infection where steroid is not appropriate |
Pros and cons checklist
- Consider allergy history — neomycin sensitivity excludes Maxitrol for some patients.
- Assess steroid potency and IOP risk — loteprednol formulations may reduce IOP rises compared with dexamethasone.
- Compare antibiotic spectrum to culture results where available to target therapy.
- Check local availability and NHS formulary recommendations before prescribing.
- If bacterial infection is unconfirmed, many clinicians prefer a short antibiotic course first, then add steroid once infection control is evident — document the discussion and plan.
Common patient questions from UK consultations
- Can I use Tobradex in pregnancy or while breastfeeding?
- Topical ocular exposure is minimal; use only if the expected benefit justifies the potential risk after discussion with the obstetrician or ophthalmologist.
- Can I wear contact lenses?
- Remove contact lenses during active infection and while using preserved formulations; consult the prescriber before resuming lens wear.
- How long until I see improvement?
- Many patients note symptom relief within 48–72 hours; complete the prescribed course unless advised otherwise by the prescriber.
Registration, MHRA and NHS prescribing framework
MHRA approval and product licensing
- Tobradex is MHRA‑approved for use in the United Kingdom and authorised as a prescription medicine.
- Suppliers must comply with labelling and leaflet requirements defined by the product licence.
NHS prescribing framework
- Prescribers should follow local formularies and antimicrobial stewardship principles when choosing combined steroid/antibiotic products.
- Tobradex is a POM and should be used where combined steroid and antibiotic therapy is justified by clinical assessment.
- Report safety events via the MHRA Yellow Card; antimicrobial stewardship teams and formularies may audit use in trusts.
Storage, handling and disposal (UK household focus)
Storage
- Store Tobradex at 2–25°C and do not freeze.
- Protect the bottle from light and keep it in the original box where possible.
- Discard the bottle 28 days after opening as per shelf‑life guidance.
- Keep all medicines out of the reach and sight of children.
Handling and disposal
- Wash hands before instillation and avoid touching the tip of the bottle to the eye or eyelid.
- Replace the cap immediately after use and do not share eye‑drop bottles with others.
- Do not flush leftover drops or bottles down the toilet; return unused or expired medicines to a pharmacy for safe disposal or use a household medicine‑take‑back event.
Practical tips for UK climate
- Avoid storing eye drops in bathrooms where heat and humidity fluctuate; a cool cupboard is preferable.
- Keep the product in its original packaging to protect from light and to retain the patient information leaflet.
- When travelling in hot weather, carry bottles in an insulated bag to protect from extremes of temperature and direct sunlight.
Guidelines for proper use and pharmacist counselling (patient safety)
UK pharmacist counselling style
- Demonstrate instillation technique: tilt head back, pull down the lower lid to form a pocket, instil one drop, close the eye gently for 1–2 minutes and apply punctal occlusion if advised.
- Warn patients that transient stinging or blurred vision may occur and advise them not to drive until vision clears.
- Advise contact lens wearers to remove lenses during active infection and while using preserved formulations, and to seek prescriber approval before resuming lens wear.
- Emphasise the intended duration of therapy and the need for review if symptoms persist beyond the expected timeframe.
NHS patient safety advice
- Monitor for red flags including worsening pain, decreased vision, severe discharge or new floaters and advise urgent assessment if these occur.
- Document informed consent when prescribing a steroid‑containing eye product and schedule review for ongoing therapy beyond two weeks.
- Report suspected side‑effects to the MHRA Yellow Card and record significant events in the patient record.
Closing practical tools
- Provide a printed patient leaflet and an instillation demonstration card at dispensing.
- Record batch number and expiry date on the dispensing record for post‑operative patients.
- Offer follow‑up or a pharmacist phone check for adherence and adverse‑effect monitoring when appropriate.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Liverpool | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Brighton | England | 9–21 days |
| Plymouth | England | 9–21 days |
Closing notes for clinicians and patients
Tobradex remains a useful combined anti‑infective and anti‑inflammatory option where bacterial infection and marked inflammation coexist, particularly in post‑operative settings.
Ensure clear documentation of indication, intended duration and follow‑up arrangements when prescribing a steroid‑containing ocular product.
Patients should be counselled on instillation technique, storage, red‑flag symptoms and the importance of review if therapy is prolonged.
Suspected adverse reactions should be reported via the MHRA Yellow Card scheme to support ongoing safety monitoring.