Trazodone
In brief
- In our pharmacy, you can buy trazodone without a prescription, with delivery available across the United Kingdom in discreet packaging; note that trazodone is a prescription-only medicine in the UK.
- Trazodone is used mainly to treat major depressive disorder and is commonly prescribed off-label for insomnia; its mechanism includes serotonin reuptake inhibition and antagonism of 5‑HT2 receptors.
- Usual doses: for depression 150 mg/day in divided doses or at bedtime (up to 300 mg/day in outpatients and 600 mg/day in hospitalised patients); for insomnia 25–100 mg at bedtime, individualised per response.
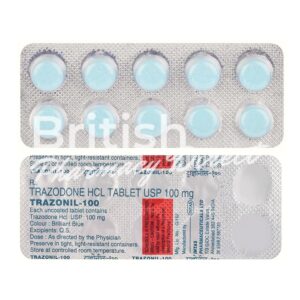
- Administered orally as capsules (50 mg, 100 mg), tablets (150 mg) or oral solution.
- Onset: sedative effects typically begin within 30–60 minutes after an oral dose; antidepressant benefits usually take 2–4 weeks to become evident.
- Duration of action varies by formulation: sedative effects commonly last about 6–12 hours; antidepressant effects require daily dosing for sustained benefit.
- Alcohol warning: avoid alcohol — combining alcohol or other CNS depressants with trazodone increases sedation, respiratory depression and risk of accidents.
- The most common side effect is sedation/drowsiness.
- Would you like to try trazodone without a prescription?
Basic trazodone information
- INN (international nonproprietary name): Trazodone
- Brand names available in the United Kingdom: Generic trazodone products
- ATC code: N06AX05
- Forms and dosages: Capsules 50 mg and 100 mg; tablets 150 mg; oral solution
- Manufacturers in the United Kingdom: Various generic manufacturers
- Registration status in the United Kingdom: Prescription-only medicine (POM)
- OTC / Rx classification: Prescription only (POM)
Critical warnings and restrictions (safety first — UK patient protection)
Who needs to read this first?
Anyone prescribed trazodone or considering it for sleep or mood symptoms should read the safety section first.
High‑risk groups (elderly, pregnancy, chronic illness)
Trazodone is a prescription‑only medicine and needs careful use in certain groups.
- Avoid or use extreme caution in recent myocardial infarction, severe hepatic impairment and acute intoxication with alcohol or other CNS depressants.
- Use caution with seizure disorders, uncontrolled bipolar disorder (risk of mania), and angle‑closure glaucoma.
- Older adults are at increased risk of orthostatic hypotension and hyponatraemia; start low and titrate slowly.
- Priapism is a rare but urgent side effect requiring immediate medical attention.
- Monitor sodium levels in older patients because of the risk of hyponatraemia/SIADH.
Monitoring checklist
- Baseline: full medical history, current medicines, ECG if significant cardiac disease or QT‑prolonging drugs.
- Within 1–2 weeks: check for excessive sedation, dizziness, orthostatic symptoms and any signs of hyponatraemia (confusion, seizures).
- At 4–6 weeks: assess mood, suicidality, blood pressure standing and supine, and consider serum sodium in older adults or those on diuretics.
- Ongoing: review for sexual side‑effects, morning sedation and falls risk at each follow‑up; document and adjust dose where needed.
Interaction with activities (driving, workplace safety under UK law)
Many people worry about safety at work and driving when starting trazodone.
Trazodone commonly causes sedation, dizziness and blurred vision, which can affect driving and safety‑critical tasks.
Do not drive / operate checklist
- Do not drive if you feel drowsy, dizzy or your reactions are slowed after taking trazodone.
- If starting or changing dose, avoid driving until you know how it affects you.
- Report any persistent sedation or visual disturbance to your prescriber before resuming driving.
Employer notification steps
- Inform your employer if you perform safety‑critical duties and experience sedation or dizziness.
- Consider occupational health advice for return‑to‑work decisions where performance or safety is affected.
Q&A — “Can I drive after taking it in the UK?”
Q: Can I drive after taking trazodone?
A: No — only if you are certain you are not drowsy or impaired.
UK law requires fitness to drive, and sedation or slowed reactions may make driving illegal and dangerous.
If you are starting trazodone or changing dose, avoid driving until you know the effect.
Report any adverse events via the MHRA Yellow Card scheme and tell your prescriber about driving issues.
Usage basics
INN, brand names available in the UK
What is the drug called and which brands might you see in pharmacy?
- INN
- Trazodone
- Brand
- In the UK trazodone is supplied as generic products (capsules, tablets and oral solution).
- Generics
- Multiple generics are supplied by various manufacturers and are commonly dispensed in UK pharmacies.
Legal classification (POM, P, GSL)
How is trazodone classified for supply?
- Trazodone is a prescription-only medicine (POM) in the UK and is not a controlled drug.
- Prescriptions may be issued on NHS or private prescription forms and can be supplied through community pharmacy, registered online pharmacies or hospital dispensaries.
- Electronic prescribing and NHS e‑prescriptions are widely used in the UK for authorised supply.
Dosing guide
Standard regimens (NHS practice and practical notes)
Patients and prescribers commonly use different regimens depending on the indication.
- For major depressive disorder in adults: typical initiation is 150 mg/day in divided doses after food or as a single dose at bedtime, with upward titration to effect.
- Outpatient maximum is usually 300 mg/day, with hospitalised patients up to 600 mg/day per SPC guidance.
- For off‑label insomnia: low bedtime doses of 25–100 mg are commonly used.
- Assess clinical response in 2–4 weeks and continue treatment for a minimum of six months after remission for depression.
Titration and monitoring checklist
- Start at the lowest effective dose for the indication and patient group.
- Increase in small increments while monitoring sedation, blood pressure and mood.
- Reassess suicidality and overall response within the first month and after dose changes.
- Document dose changes and rationale in the medical record.
Adjustments for comorbidities
Are dose changes needed for specific patients?
- Children: safety and efficacy not established; use is generally not recommended.
- Elderly: start low (often 50 mg at night for insomnia), titrate slowly and monitor for orthostatic hypotension and hyponatraemia.
- Hepatic or renal impairment: use lower initial doses and watch for accumulation and increased adverse effects.
Q&A — “What if I miss a dose?”
Q: What should I do if I miss a dose?
A: Take it as soon as you remember unless it is near the time of the next dose — do not double the dose.
For insomnia dosing, skip the missed bedtime dose and take the next dose as scheduled the following night.
If unsure, contact your GP or pharmacist for advice tailored to your regimen.
Interaction chart (what to avoid or check)
Food and drinks
Some common items you might pair with medication can change how you feel on trazodone.
| Food/drink | Effect |
|---|---|
| Alcohol | Increases sedation and risk of respiratory depression; acute alcohol intoxication is an absolute contraindication. |
| Caffeine | May reduce perceived sedation but will not prevent adverse effects; use caution if caffeine affects sleep. |
| Grapefruit juice | May increase levels of CYP3A4 substrates; exercise caution with regular consumption. |
Common drug conflicts
Drug interactions can increase risk of serious adverse reactions.
| Concomitant drug | Issue |
|---|---|
| MAOIs | Risk of severe serotonin syndrome; do not combine. |
| SSRIs, SNRIs, other serotonergic drugs | Increased risk of serotonin syndrome; monitor closely and report suspected reactions to the MHRA Yellow Card scheme. |
| CYP3A4 inhibitors (e.g. ketoconazole, some macrolides) | Can raise trazodone plasma levels and increase adverse effects. |
| QT‑prolonging drugs and CNS depressants | Increased risk of arrhythmia or excessive sedation; review ECG if cardiac risk exists. |
Urgent action checklist
- Stop combined use immediately if signs of serotonin syndrome develop (high temperature, agitation, rigidity, rapid heart rate).
- Seek urgent medical care for suspected overdose or severe interactions.
- Report suspected adverse drug reactions to the MHRA Yellow Card scheme.
Legal status and availability in the UK
In our online pharmacy, trazodone is available without a prescription, with discreet delivery to the United Kingdom in 5‑14 days.
Mechanism and pharmacology
Simplified explanation
How trazodone works in plain clinical terms.
- SARI
- Serotonin antagonist and reuptake inhibitor — it inhibits serotonin reuptake while antagonising 5‑HT2 receptors, producing antidepressant and sedative effects.
- Alpha‑1 blockade
- Contributes to orthostatic hypotension and dizziness, especially when standing.
- Antihistaminic activity
- Explains the sedative and sleep‑promoting properties at low doses.
Clinical terms and classification
Key pharmacokinetic points that affect prescribing and interactions.
- ATC: N06AX05.
- Metabolism: primarily hepatic via CYP3A4; CYP3A4 inhibitors and inducers can alter plasma levels.
- Clinical consequences: adjust dose for hepatic impairment and monitor for increased sedation or adverse effects when combined with CYP3A4 inhibitors.
Indications and off‑label uses
MHRA‑approved uses
What trazodone is licensed for in the UK.
In the UK trazodone is licensed for depressive illness (including depression accompanied by anxiety) and for anxiety; UK prescribers follow BNF and NICE guidance for treatment hierarchies.
Off‑label practices in NHS and private care
Common off‑label reasons prescribers choose trazodone.
- Low‑dose nocturnal therapy for insomnia, particularly when comorbid depression or SSRI‑induced insomnia exists.
- Adjunctive use for anxiety‑related sleep disturbance or as an adjunct in pain clinics in selected cases.
Documentation checklist for off‑label use
- Record the rationale for off‑label prescribing in the clinical notes.
- Discuss risks and expected benefits with the patient and document informed consent.
- Plan monitoring intervals and review outcomes objectively.
Alternatives matrix
NHS prescribing alternatives (comparison table)
| Drug | Typical starting dose | Sedative effect | Main risks | Monitoring needs |
|---|---|---|---|---|
| Sertraline (SSRI) | 50 mg daily | Low | Sexual dysfunction, GI upset | Monitor mood, suicidality |
| Escitalopram (SSRI) | 10 mg daily | Low | QT considerations at high doses, sexual side‑effects | ECG if cardiac risk |
| Mirtazapine | 15 mg nightly | High (sedating) | Weight gain, increased appetite | Monitor weight and lipids |
| Amitriptyline (TCA) | 10–25 mg at night (for insomnia/off‑label) | High | Anticholinergic effects, orthostatic hypotension, cardiac risk | ECG in older adults, BP |
Pros and cons checklist
- Consider prior treatment history when switching: inadequate response, tolerability and side‑effect profile steer the choice.
- Match sedative properties to patient needs: mirtazapine or low‑dose amitriptyline for marked insomnia, trazodone for combined sleep and depressive symptoms.
- Discuss childbearing plans, as some antidepressants have pregnancy considerations; involve specialist perinatal mental health services where appropriate.
Common questions
- Will it make me sleepy all day?
Often initially yes; timing the dose at night and using the lowest effective dose reduces daytime sedation.
- How long before it works for depression?
Expect initial improvements in 2–4 weeks, with full response taking longer; continue for a minimum six months after remission.
- Is it safe in pregnancy?
Limited data exist; discuss risks and benefits with your prescriber and seek specialist maternal mental health advice if pregnant or planning pregnancy.
- What to do if sexual side‑effects occur?
Speak with your GP about alternative treatments or dose adjustments; options include switching class or reviewing adjunct strategies.
For specialist advice, contact NHS Mental Health services or local perinatal mental health clinics where appropriate.
Registration and regulation
MHRA approval process (brief practical)
How regulatory documents guide safe use.
- Marketing authorisations require regulatory review; consult the SPC and PIL for brand‑specific dosing and contraindications.
- Report adverse drug reactions to the MHRA Yellow Card scheme.
- Regulatory documents to check: SPC, PIL and the BNF entry for trazodone.
NHS prescribing framework
Prescribing should follow recognised guidance and be documented.
- Align prescribing with NICE, the BNF and local formularies where available.
- Document indication, informed consent for off‑label use and a monitoring plan in the clinical record.
- Follow local audit and governance processes for repeat prescribing and review intervals.
Storage and handling (UK household and pharmacy guidance)
UK household storage (cold/damp climate considerations)
How to keep trazodone safe at home.
- Store at room temperature between 15–30°C in the original packaging.
- Avoid bathroom cupboards where humidity fluctuates and can damage tablets.
- Keep out of reach of children and pets and use locked storage if household safety is a concern.
Guidance from NHS and pharmacists
- Return unused or expired medicines to any community pharmacy for safe disposal; do not flush down the toilet.
Guidelines for proper use (pharmacist and patient safety checklist)
UK pharmacist counselling style
Essential counselling points to cover at supply.
- Explain the indication, expected onset and that response for depression may take 2–4 weeks.
- Highlight common side‑effects: sedation, dizziness and dry mouth.
- Warn about rare but serious risks such as priapism and hyponatraemia and the need for urgent care if these occur.
- Discuss interactions with alcohol, MAOIs, SSRIs and CYP3A4 inhibitors and driving safety.
- Provide the PIL and document that counselling was given.
NHS patient safety advice
- Arrange GP follow‑up within 2–4 weeks after initiation or dose change to review mood and side‑effects.
- Monitor mood and suicidal thoughts, especially in younger adults and after dose changes.
- Check blood pressure standing and supine if symptomatic and request serum sodium testing in older patients if clinically indicated.
- Taper gradually when stopping to reduce the risk of withdrawal symptoms.
- Contact list: GP, NHS 111 for urgent non‑emergency advice, 999 for emergency symptoms, and report adverse reactions via the MHRA Yellow Card.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 5‑7 days |
| Birmingham | England | 5‑7 days |
| Manchester | England | 5‑7 days |
| Glasgow | Scotland | 5‑7 days |
| Leeds | England | 5‑7 days |
| Edinburgh | Scotland | 5‑7 days |
| Liverpool | England | 5‑7 days |
| Bristol | England | 5‑7 days |
| Newcastle Upon Tyne | England | 5‑9 days |
| Nottingham | England | 5‑9 days |
| Southampton | England | 5‑9 days |
| Leicester | England | 5‑9 days |
| Coventry | England | 5‑9 days |
| Bradford | England | 5‑9 days |