Florinef
In brief
- In our pharmacy, you can buy Florinef without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Florinef (fludrocortisone acetate) is a synthetic corticosteroid with strong mineralocorticoid activity, used for mineralocorticoid replacement in adrenal insufficiency and certain salt‑wasting states.
- A typical adult starting dose is 100 mcg (0.1 mg) once daily; maintenance dosing usually lies between 50 mcg and 200 mcg per day depending on the indication and clinical response.
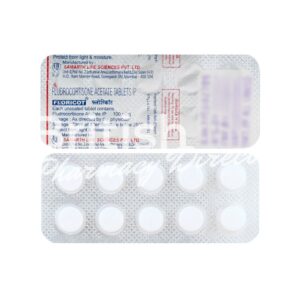
- The form of administration is oral: 100 microgram (0.1 mg) tablets.
- Clinical effects on blood pressure and symptoms often occur within days of starting treatment.
- Limit alcohol while taking Florinef, as alcohol can worsen blood pressure control.
- Possible side effects include fluid retention, weight gain, raised blood pressure and low potassium (hypokalaemia), so regular monitoring is needed.
- Would you like to try Florinef without a prescription?
Basic Florinef information
- INN (international nonproprietary name): fludrocortisone (as fludrocortisone acetate)
- Brand names available in the United Kingdom: Florinef; generic fludrocortisone
- ATC code: H02AA02
- Forms and dosages: tablets 100 micrograms (0.1 mg)
- Manufacturers in the United Kingdom: fludrocortisone 100 microgram tablets are supplied by several manufacturers
- Registration status in the United Kingdom: licensed by the MHRA; prescription only
- OTC / Rx classification: Prescription-only medicine (POM)
Safety, warnings and patient protection
Worried about safety when starting a medicine for low blood pressure or adrenal support?
Fludrocortisone is a potent mineralocorticoid and must be treated with care.
Incorrect use risks fluid overload, hypertension, heart failure and low potassium (hypokalaemia).
UK patients must have baseline and periodic monitoring including blood pressure, electrolytes and renal function.
Weight should be checked regularly because fluid retention can be an early sign of harm.
Everyone starting replacement therapy should receive clear written action plans for dose changes and sick‑day rules.
Pregnancy and breastfeeding precautions are essential and liaison with obstetric and endocrine teams is recommended.
Record allergy status and any concurrent systemic corticosteroid use before prescribing.
Community pharmacists should add alert flags in the NHS Summary Care Record where appropriate.
Suspected adverse drug reactions should be reported via the MHRA Yellow Card scheme.
Store medicines securely and out of reach of children and carry an emergency steroid card if on replacement therapy.
- Monitoring schedule: Baseline BP (supine/standing), U&Es, renal function and weight before starting.
- Monitoring schedule: Repeat tests 1–2 weeks after any dose change and then at clinically appropriate intervals (commonly 3–6 monthly once stable).
- Red-flag symptoms: New or worsening breathlessness, swelling of legs, sudden weight gain, chest pain, severe headache, fainting or severe muscle weakness.
- Emergency contacts: GP surgery, out-of-hours service, NHS 111 for urgent advice and 999 for life‑threatening problems.
Pre-prescription baseline tests checklist:
- Blood pressure supine and standing.
- Urea and electrolytes (including potassium and sodium).
- Renal function (eGFR).
- Baseline weight and fluid status.
- Allergy history and current steroid use.
Usage basics: INN and brand names available in the UK
Patients often ask what florinef actually is and how it is supplied.
The active compound for Florinef is fludrocortisone acetate, commonly given as 0.1 mg (100 mcg) tablets under the brand name Florinef.
Packaging for Florinef in the UK is typically in small packs suitable for specialist or repeat prescriptions, commonly from 28 to 100 tablets depending on supplier.
Florinef is classified as a prescription‑only medicine (POM) under UK law and must be issued via NHS electronic prescription or a private prescription.
- UK brand examples: Florinef (fludrocortisone acetate) — commonly 100 mcg tablets.
- Pack sizes: Frequently supplied in 28, 30, 60 or 100 tablet packs depending on source.
- Legal classification: Prescription‑Only Medicine (POM).
- INN
- Fludrocortisone acetate.
- Class
- Synthetic steroid with predominant mineralocorticoid activity.
Remember to check MHRA product details and local NHS formularies before prescribing or dispensing.
Dosing guide (NHS practice) and adjustments for comorbidities
Many patients ask how much Florinef to take and how changes are managed.
A typical adult starting dose is 100 mcg (0.1 mg) once daily, adjusted according to symptoms and investigations.
Maintenance dosing usually lies between 50 mcg and 200 mcg per day depending on the indication and clinical response.
For paediatric patients and the elderly, clinicians generally start at lower doses and titrate cautiously under specialist supervision.
Reduce or stop treatment if heart failure worsens, hypertension is uncontrolled, renal function falls significantly or hypokalaemia develops.
Concurrent systemic corticosteroids may increase mineralocorticoid load and require dose review.
- Titration steps: Start 100 mcg daily, reassess symptoms and BP after 1–2 weeks, adjust by 50 mcg increments where needed.
- Monitoring frequency: BP and electrolytes 1–2 weeks after initiation or dose change, then as clinically indicated.
Baseline tests checklist:
- BP measured supine and standing.
- Urea and electrolytes including sodium and potassium.
- Weight and clinical assessment for oedema.
- ECG if cardiac risk factors or significant electrolyte disturbance is suspected.
Q&A — “What if I miss a dose?”
Q: What should I do if I miss a dose of fludrocortisone?
A: Take the dose as soon as you remember the same day and do not double up to make up missed doses.
A: If more than 24 hours have passed, contact your clinician for guidance rather than adjusting long‑term replacement doses yourself.
A: Seek urgent advice if you develop dizziness, fainting or sudden salt craving after a missed dose.
Interaction chart: food, drink and common drug conflicts; MHRA considerations
People often want to know what they can safely take with Florinef.
Food has little direct effect on absorption, but sodium intake and use of diuretics strongly influence clinical response.
Alcohol can worsen blood pressure control and should be limited while on mineralocorticoid therapy.
CYP interactions are limited, but combining Florinef with systemic corticosteroids increases mineralocorticoid activity.
| Drug | Effect | Risk | Action |
|---|---|---|---|
| Loop and thiazide diuretics | Increase potassium loss | Hypokalaemia | Monitor U&Es frequently; consider potassium supplements if needed. |
| ACE inhibitors / ARBs | Alter blood pressure response | Variable potassium changes; hypotension risk | Monitor BP and electrolytes; adjust doses if needed. |
| Systemic corticosteroids | Add mineralocorticoid effect | Fluid overload, hypertension | Review total steroid load; liaise with prescribing teams. |
| NSAIDs | Affect renal perfusion | Worsening renal function and electrolyte imbalance | Use lowest effective dose and monitor renal function. |
- Report unexpected severe adverse reactions such as hypertensive crisis, heart failure or severe hypokalaemia to MHRA via Yellow Card.
- Review over‑the‑counter medicines for NSAID content and decongestants that can change BP.
- High sodium intake will amplify Florinef effects and should be discussed with clinician.
High-risk groups and activity interactions
High-risk groups
Elderly patients are more vulnerable to fluid retention, heart failure and declining renal function and require lower starting doses and closer monitoring.
During pregnancy Florinef should be used only if benefits outweigh risks and with joint care from obstetric and endocrine teams.
Patients recovering from severe respiratory infections or with ischaemic heart disease, uncontrolled hypertension, hepatic impairment or a history of thromboembolism require specialist review before starting.
Interaction with activities (driving, workplace safety under UK law)
Fludrocortisone can cause dizziness or visual disturbance related to blood pressure changes and anyone affected must not drive or operate machinery until symptoms resolve.
Safety‑critical workers should discuss fitness to work with occupational health and document any work restrictions.
Q&A — “Can I drive after taking it in the UK?”
Q: Can I drive after starting fludrocortisone?
A: If you feel well and have no dizziness you may drive.
A: If you experience faintness, severe dizziness or visual disturbances do not drive and inform DVLA or occupational health if problems persist.
- Red-flag symptoms for driving: Syncope, repeated dizziness on standing, visual disturbance or marked weakness.
Legal status and availability in the UK
In our online pharmacy, Florinef is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Mechanism of action and pharmacology
People want a simple explanation of how the drug works.
Fludrocortisone is a synthetic corticosteroid with strong mineralocorticoid effects that increases sodium reabsorption and potassium excretion in the kidney.
By expanding plasma volume it raises blood pressure and helps correct salt‑wasting in adrenal insufficiency.
Clinically it binds mineralocorticoid receptors in the distal tubule and collecting duct, increasing ENaC activity and Na+/K+ ATPase function.
At higher doses fludrocortisone also has some glucocorticoid receptor activity.
The half‑life and pharmacodynamics allow once‑daily dosing for many patients but electrolyte and BP effects require careful titration.
- Mechanism
- Increases renal sodium reabsorption and potassium excretion via mineralocorticoid receptor activation.
- Onset
- Clinical effects on BP and symptoms often occur within days; electrolyte changes can be rapid.
- Monitoring measures
- BP, weight, serum sodium and potassium, renal function.
Bear in mind that renal impairment and concurrent steroid therapy change both effect and safety profile.
Indications and off‑label uses in NHS and private care
Which conditions is Florinef used for on the NHS?
MHRA‑recognised indications include mineralocorticoid replacement in primary or secondary adrenal insufficiency and certain salt‑wasting states.
On both NHS and private practice, clinicians may also use fludrocortisone in some autonomic failure syndromes, usually under specialist supervision.
Off‑label use may include refractory orthostatic hypotension when non‑drug measures have failed and after specialist review.
- Approved indications: Mineralocorticoid replacement for adrenal insufficiency and specific salt‑wasting disorders.
- Common off‑label uses: Autonomic failure syndromes and refractory orthostatic hypotension.
Checklist for prescribers considering off‑label use:
- Confirm diagnosis with appropriate tests.
- Obtain baseline investigations and document informed consent for off‑label prescribing.
- Arrange a clear follow‑up plan and monitoring schedule.
Specialist oversight is recommended for paediatric and pregnancy prescribing.
Alternatives matrix: NHS prescribing alternatives and pros/cons checklist
Patients often ask what other options exist besides Florinef.
For symptomatic orthostatic hypotension, first‑line measures include increased salt and fluid intake, compression garments and review of causative medicines.
The main pharmacological alternative is midodrine, which has a different mechanism and monitoring needs.
| Alternative | Mechanism | Pros | Cons | Monitoring needs |
|---|---|---|---|---|
| Midodrine | Alpha‑agonist vasoconstrictor | Improves standing BP rapidly | Can cause supine hypertension; short half‑life requires multiple daily dosing | BP monitoring, especially supine and standing |
| Compression stockings / non‑pharmacological | Reduce venous pooling | Low adverse effects; easy to combine | Variable adherence; may be poorly tolerated in hot weather | Symptom review and adherence checks |
- Pros/cons checklist: Efficacy, side‑effect profile, monitoring burden and suitability given comorbidity.
- Stepwise approach: Start with lifestyle measures and medication review, progress to pharmacotherapy with specialist input where needed.
Common questions from UK patient consultations
Patients regularly ask a similar handful of practical questions.
- Will I gain weight? — Fluid retention and modest weight gain are possible; monitoring and dose adjustment usually control this.
- How often are blood tests needed? — Baseline, 1–2 weeks after any dose change, then periodic checks typically every 3–6 months once stable.
- Can I stop it suddenly? — No; abrupt cessation in adrenal replacement can risk adrenal crisis; follow your clinician’s tapering plan.
- Is it safe with my other medicines? — Always review with prescriber or pharmacist; particular caution with diuretics, ACEi/ARBs and NSAIDs.
Checklist of what to bring to appointments:
- Current list of medicines and supplements.
- Blood pressure diary with supine and standing readings if available.
- Symptom log showing dizziness, fainting or salt cravings.
Signpost patients to the MHRA Yellow Card site for reporting adverse reactions and NHS 111 for urgent advice.
Registration, regulation and pharmacovigilance
Healthcare professionals must follow MHRA guidance and local NHS shared‑care frameworks when prescribing and transferring care.
Fludrocortisone products authorised in the UK are POM and clinicians should follow the SPC for dosing and safety information.
Report suspected adverse reactions including heart failure exacerbation, hypertensive emergency or severe hypokalaemia to the MHRA Yellow Card system.
- Reporting steps: Document event, gather batch and product details and submit Yellow Card online or via the app.
- Required documentation for shared care: Diagnosis, current dose, monitoring schedule, emergency plan and contact details for specialist.
Prescribers should include clear responsibilities and monitoring arrangements when transferring prescribing to a GP.
Storage, handling and UK patient safety counselling
Patients often ask how to store their tablets and what to watch for at home.
Store tablets at room temperature below 25°C and protect from moisture.
Keep the medicine in its original packaging and out of reach of children.
Do not use beyond the expiry date.
A pharmacist counselling style should confirm the indication, review concurrent medications and provide written sick‑day rules and an emergency steroid card.
Teach patients to monitor BP and weight and to seek immediate care for severe breathlessness, chest pain, fainting or marked oedema.
- Counselling points: Indication, dose, expected benefits, when to check BP, signs of fluid overload and when to seek urgent help.
- Red flags: Rapid weight gain, worsening breathlessness, chest pain, fainting or severe muscle weakness.
- Monitoring calendar template: Baseline, 1–2 weeks post‑start/change, then 3 monthly until stable.
Recommend follow‑up within 1–2 weeks after initiation or dose change and provide patient leaflets where available.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Manchester | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Leicester | England | 9–21 days |